

Request an appointment
No referral needed. A real person calls you back, usually within two business hours.
Connellsville, PA · Services
Spinal manipulation in Connellsville.
A quick, small, specific technique applied to one spinal segment by a licensed physical therapist, after an evaluation that screens whether it is appropriate at all. One tool inside a plan, never an appointment on its own.
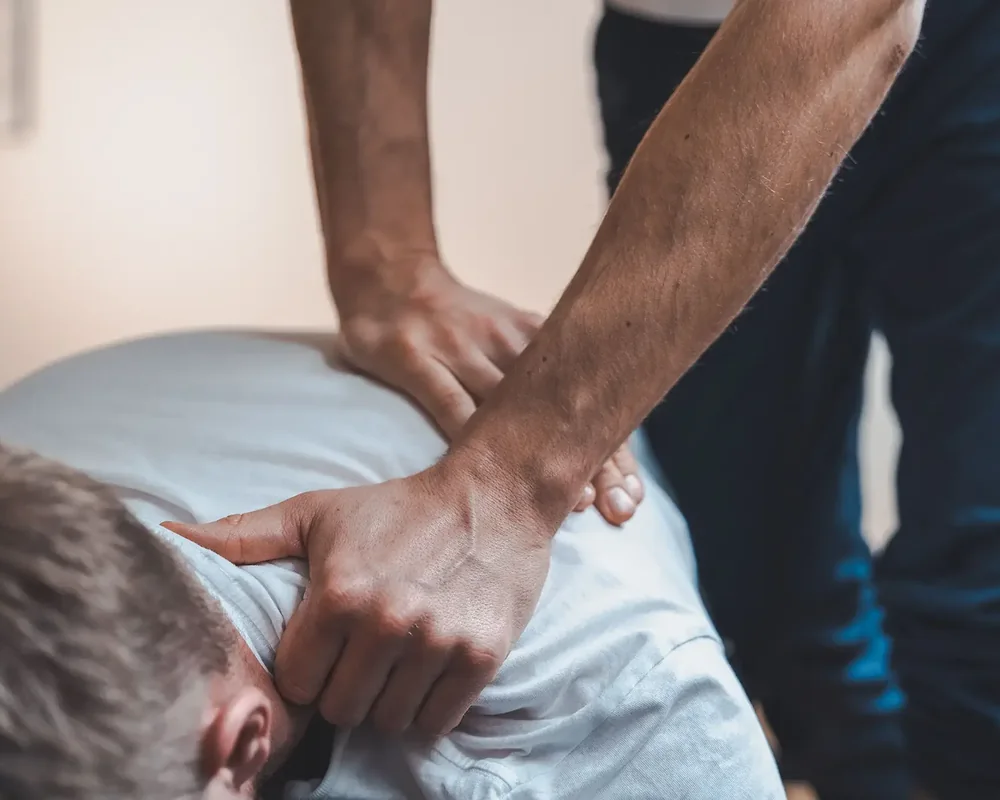
What is spinal manipulation in Connellsville?
Spinal manipulation is a hands-on technique in which a licensed physical therapist applies a quick, small, controlled force to a specific segment of the spine at the end of its available range. You may hear it called a thrust technique. It sometimes produces an audible pop, which is a pressure change inside the joint and not a bone being put back where it belongs. The pop is not the point, and a technique that makes no sound at all can work perfectly well.
What it is for is narrow and worth stating narrowly: restoring movement at a segment that testing found restricted, and settling pain enough that the rest of the visit can do its work. The evidence behind it is strongest for mechanical neck and low back pain. It is a musculoskeletal technique, and we make no claims about anything outside that. If someone tells you a spinal technique treats conditions unrelated to the musculoskeletal system, that is not a claim you will hear in this building.
So it never stands alone here. It is used inside an existing physical therapy plan, after a cause-first evaluation, and it is followed in the same visit by the mobility and strength work that addresses why the segment stiffened in the first place. Pain, Prime, Perform, Prevent: manipulation earns its place in the first two phases and then hands off. Dr. Jarrod King is a certified primary spine practitioner through the University of Pittsburgh, earned in 2019, and a board-certified orthopaedic clinical specialist, earned in 2017.
Calm it down.
Hands-on treatment begins at the first visit. You leave understanding what’s actually going on, and you feel a difference early.
Restore what’s stuck.
Targeted mobility work for the joints and tissue actually holding you back, dosed to your body, not a printed sheet.
Build strength you trust.
Progressive load against standards you have to clear before moving on. Confidence, here, is a training effect.
Make it stay fixed.
Testing before you’re cleared, then a keep-it-gone program sized to your real week. Then we graduate you.
What conditions does spinal manipulation help with?
It is used for mechanical spine problems, where testing finds a specific segment that has stopped moving well and nothing in the screening rules the technique out. A sample of what it commonly supports:
Back pain & sciatica ⟶
The stiff hinge low in the back, and the morning that takes ten minutes before it will bend.
02Neck pain ⟶
The segment that stopped rotating and made checking the left mirror a whole-body movement.
03Headaches ⟶
The kind that starts in a stiff neck and arrives behind one eye by the end of the afternoon.
04Chronic pain ⟶
A long-standing mechanical back or neck problem that has been managed rather than moved.
A spinal segment that stops moving does not stay a local problem for long. The segments above and below take on the range it gave up, the muscles around it stay switched on to guard it, and the stiff morning you have learned to work around gradually turns into the reason one whole side of your back gets loud on an ordinary Tuesday.
What does a spinal manipulation session look like?
The technique is a short part of a longer visit. Your therapist positions you, takes the segment out to the end of its available range, and applies a quick, small force. That part takes a second or two. Most people describe pressure and then a release rather than pain, and many notice more movement immediately afterward. The rest of the hour goes to the mobility and strength work that has to follow, because a segment that moves better and then goes home unused tends to stiffen back up within days.
Before any of it happens, you get screened, and the screening is not a formality. Your therapist reviews your history, checks neurological signs, and works through the specific conditions that make manipulation the wrong choice. If you are screened out, you get told so directly, and your plan uses other techniques to reach the same range. Nothing about that changes how long your visit runs. You can also simply decline the technique. Nobody here will treat that as a problem.

Who spinal manipulation is for, and who it isn’t.
It tends to fit mechanical neck and back pain where the evaluation finds a specific segment that has lost movement and the screening turns up nothing that rules the technique out. It is most useful early, in Pain and Prime, when stiffness and guarding are the things stopping the movement work from getting anywhere. It is one option among several, and there is always another way to reach the same range if it is not the right one for you.
If you want to know exactly what the technique does and what it does not do before anyone touches your spine, you are asking the right question, and the honest answer is short. It restores movement at a segment and buys a window for the rest of the plan. Nothing more than that is claimed here, and you are entitled to hear that before you agree to it.
It is not appropriate where there is osteoporosis or significantly reduced bone density, a fracture or suspected fracture, spinal instability, inflammatory arthritis affecting the spine, certain vascular conditions, progressive neurological signs, recent spinal surgery, or an unexplained symptom pattern that belongs with a physician first. Your therapist screens for every one of those before the technique is ever offered, which is exactly why it is not something you can book off a menu.
Good fit
- Mechanical neck or back pain with a specific segment that has lost movement
- Early in a plan, where stiffness and guarding are blocking the movement work
- Inside an existing physical therapy plan, followed by exercise the same visit
- A screening evaluation that turns up nothing ruling the technique out
Not the right fit
- Reduced bone density, fracture or suspected fracture, or spinal instability
- Inflammatory arthritis of the spine, certain vascular conditions, recent spinal surgery
- Progressive neurological signs, or an unexplained pattern that belongs to a physician first
- Anyone who would rather not have it: other techniques reach the same range
Manual therapy ⟶
The wider set of hands-on techniques this one belongs to, graded and retested.
02Physical therapy ⟶
The cause-first evaluation and the plan the technique is used inside of.
03Orthopedic therapy ⟶
Joint-by-joint measurement for the mechanics around the segment that stopped moving.
04Dry needling ⟶
For the guarding muscle that keeps pulling the segment straight back to stiff.
Manipulation opens a window. The work in the same visit is what keeps it open. See the full list of services.
“Very friendly, knowledgeable staff. Therapists truly listen to problems and actively work to resolve them! Highly recommended!”Camille S. · Patient review
Questions, answered plainly.
The technique itself overlaps a great deal. What differs is the setting it sits inside. Here, manipulation is one tool within a physical therapy plan, selected after a cause-first evaluation and followed in the same visit by the movement and strength work meant to keep the segment moving. It is not sold as a standalone appointment or as an open-ended schedule of visits on its own.
Most people describe pressure and then a release rather than pain, and the technique itself takes a second or two. The pop is a pressure change inside the joint, not a bone going back into place, and it is not the goal. Plenty of effective techniques make no sound at all. Mild soreness for a day afterward is possible and usually settles on its own.
It is performed only by a licensed physical therapist and only after an evaluation that screens for the conditions that make it the wrong choice, among them reduced bone density, fracture, spinal instability, inflammatory arthritis affecting the spine, certain vascular conditions, progressive neurological signs and recent spinal surgery. If you are screened out, or if you would simply rather not have it, your plan uses other techniques to restore the same movement.
No. It is scheduled inside an existing physical therapy plan rather than as a standalone appointment, because the technique opens a window and the exercise that follows is what keeps it open. Your evaluation decides whether it belongs in your plan at all. No referral is needed to book that evaluation, since Pennsylvania allows direct access.
Start with the evaluation that decides whether it fits.
Put it in writing.
Six short questions. A real person calls you back, usually within two business hours, with times that fit your week.
The people who end up filling this out are rarely in the worst pain of their life. They’re just done working around it, done picking the errand that doesn’t require the stairs. If that’s the stage you’re at, this is the part where you stop researching and start.
Consider it filed.
A real person will call you back, usually within two business hours, with appointment times that fit your week. Keep your phone nearby.
Can’t wait? Call (724) 628-7288 ⟶Two clinics. Same standard in both.
Connellsville and Scottdale, both fully staffed, both easy to park at. Come see either one before you commit, if you like.
Clinic 01 · Connellsville
Directions to Connellsville ⟶ (opens in a new tab)
Clinic 02 · Scottdale
Directions to Scottdale ⟶ (opens in a new tab)